A thread-like red vessel, a blue reticular vein and a rope-like bulging vein do not point to the same treatment. By matching appearance with duplex-ultrasound findings, symptoms, vein anatomy and recovery preferences, you can compare conservative care, injections, laser, radiofrequency treatment, phlebectomy and surgery more sensibly.
Key takeaways
- Match treatment to vein width, depth, shape and symptoms.
- Ultrasound helps identify superficial venous reflux before ablation or surgery.
- Sclerotherapy suits many small surface veins; larger tortuous veins need different planning.
- Seek urgent care for sudden leg swelling, chest pain or breathlessness.
Spider veins, reticular veins and varicose veins need different answers
Look at the vein’s width, shape, depth and symptoms before comparing treatments. Spider veins are fine red, blue or purple lines that branch across the skin. Varicose veins are wider, raised and twisted, and they may cause aching, heaviness, itching or ankle swelling.
| Type | What you see or feel | What it may indicate |
|---|---|---|
| Spider veins | Flat, thread-like clusters close to the skin, usually under 1 mm wide | A surface cosmetic concern, though a deeper feeder can exist |
| Reticular veins | Flat blue-green veins, about 1–3 mm wide, often beneath spider veins | A feeding surface vein or early venous disease |
| Small surface varicosities | Raised, branching veins larger than reticular veins but not rope-like | Local tributary veins that may connect to a refluxing trunk |
| Varicose veins | Bulging, tortuous, rope-like veins, often over 3 mm wide | Possible reflux in a larger superficial vein |
Appearance cannot prove where blood is flowing backward. Duplex ultrasound maps reflux, checks whether deep veins are open, and shows whether a visible vein is fed by an incompetent trunk. That distinction matters: treating spider veins without addressing significant reflux can leave the cause in place.
A useful varicose veins treatment comparison therefore starts with the vein type and its source, not a photograph alone. Knowing whether you have spider veins or varicose veins helps narrow the discussion, but ultrasound may change the answer.
What a specialist checks before recommending a procedure
A visible vein needs a clinical examination and duplex ultrasound before treatment when it is large, tortuous, painful, swollen, recurrent, or accompanied by skin changes. Appearance alone cannot show whether a larger incompetent vein is feeding it.
- The specialist records aching, heaviness, itching, night cramps, bleeding, previous clots, ulcers, pregnancy, and earlier vein procedures.
- The leg is examined while you are standing. The clinician checks vein patterns, swelling, skin colour, eczema, ulcers, tenderness, and pulses.
- Duplex ultrasound maps blood flow. It shows which superficial veins have reflux, whether the deep veins are open, the vein’s diameter, the affected segment, and whether a visible branch connects to an incompetent truncal vein.
- The recommendation then accounts for vein tortuosity, access for a catheter, skin and nerve risks, previous treatment, anaesthesia preferences, and recovery time.
A small spider vein with no symptoms may not need duplex scanning before cosmetic treatment, but scan first if clusters keep returning, symptoms extend beyond the visible marks, or bulging veins are present. Treating surface vessels alone can leave significant reflux untreated.
During pregnancy, intervention is generally deferred; symptom-directed compression and review after delivery are the usual approach. In Mumbai, ChirayuHealthcare Polyclinic&Diagnostics can help you confirm whether your appointment includes both examination and duplex mapping before you choose treatment options.
Related products
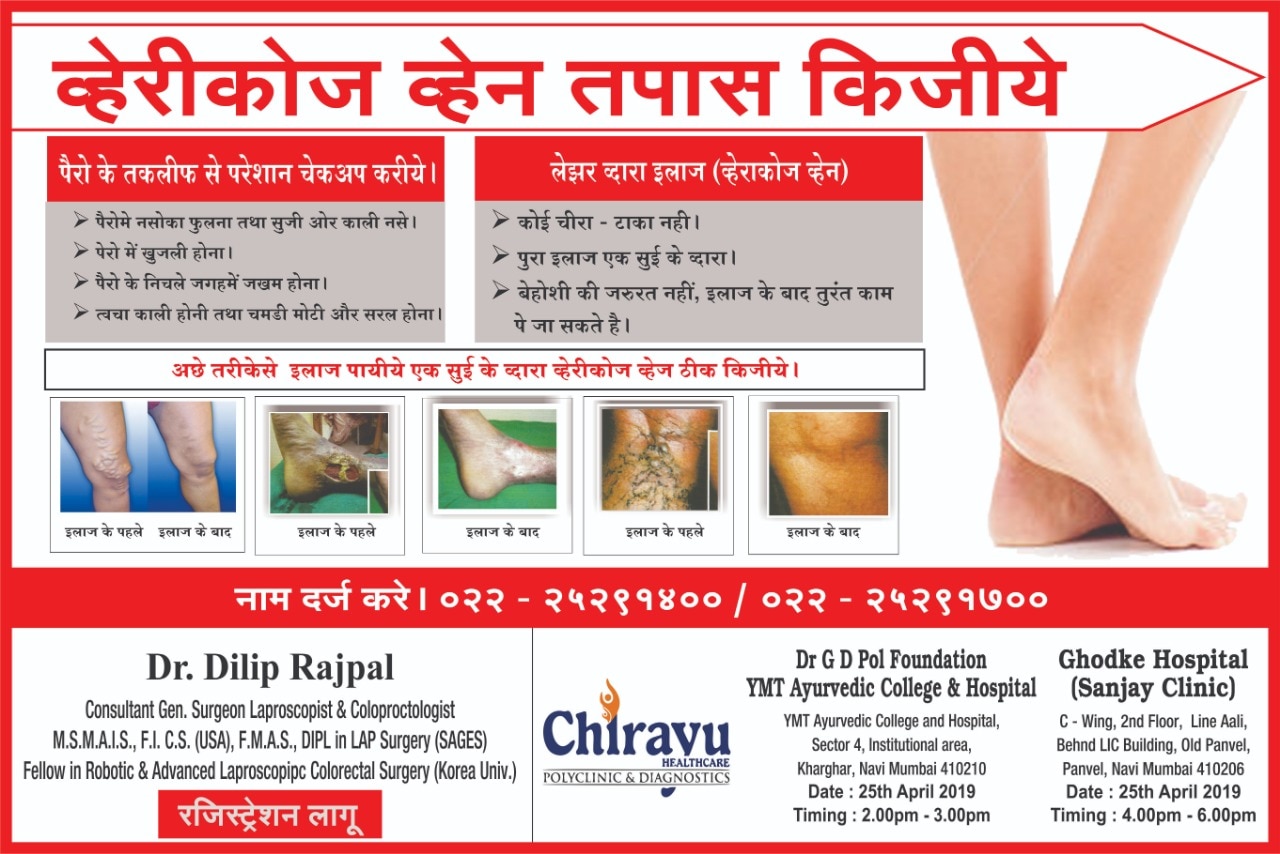 | What are varicose veins? Varicose veins in legs An example of varicose veins in the leg. View product → |
 | Laser varicose veins surgery Laser varicose vein surgery is a procedure that uses heat from a laser to reduce varicose veins. View product → |
Which treatments suit small, surface and tortuous veins
Small, flat spider and reticular veins usually suit injection or surface treatment; bulging, rope-like veins need a different approach. This varicose veins treatment comparison focuses on visible veins, not confirmed truncal reflux.
| Option | Best fit | Main trade-off |
|---|---|---|
| Compression | Aching or swollen legs when you want symptom relief without a procedure | Supports circulation but does not close or remove a vein |
| Observation | Small, stable, painless veins that do not trouble you | The vein remains, and new veins can appear |
| Liquid sclerotherapy | Spider veins and small reticular veins | Precise for narrow vessels, but several sessions may be needed |
| Foam sclerotherapy | Larger tributaries, medium varicosities and winding veins | Reaches tortuous channels that a straight catheter cannot, though residual or recurrent veins are common |
| Surface laser | Very fine, superficial spider veins, especially when avoiding injections | Suits tiny surface vessels, not deep or bulky varicosities; skin colour changes and repeated treatment are possible |
| Ambulatory phlebectomy | Localised, palpable, tortuous bulges close to the skin | Removes targeted tributaries through tiny punctures, but requires local anaesthetic and wound care |
A specialist may combine methods: foam for a winding tributary, then phlebectomy for remaining bulges. Surface laser vein treatment choices are not substitutes for checking a feeder vein; significant reflux can keep visible veins returning after surface treatment.
Compression or observation fits appearance-only concerns, but pain, swelling, skin changes or rapid enlargement justify reassessment before treatment. No option prevents reflux from developing in another vein.
Laser, radiofrequency ablation or surgery for superficial reflux
Once duplex ultrasound confirms reflux in a larger superficial trunk, endothermal treatment is usually considered before surgery. Endovenous laser ablation (EVLA) and radiofrequency ablation (RFA) seal the faulty vein from inside, allowing blood to return through healthier veins.
| Option | How it works | Main trade-off |
|---|---|---|
| Endovenous laser ablation | A laser fibre heats and closes the vein through a needle puncture, usually under local anaesthetic. | Requires catheter access; heat can cause bruising, tenderness or nearby-nerve irritation. |
| Radiofrequency ablation | A radiofrequency catheter delivers controlled heat to close the vein through a puncture. | Similar access and recovery demands to EVLA; anatomy still determines whether the catheter can reach the whole segment. |
| Conventional surgery | Ligation ties off the vein and stripping removes it through incisions. | Useful when catheter access is difficult, but usually means more wounds and a longer recovery. |
EVLA and RFA are both laser vein treatment choices for a straight, accessible refluxing trunk. Neither is automatically best: vein diameter, tortuosity, the refluxing segment, previous procedures, skin or nerve risk, anaesthesia preferences and recovery plans all matter.
Ask a varicose veins specialist for treatment options based on the scan, not on the largest visible bulge. If endothermal access is unsuitable, NICE places ultrasound-guided foam sclerotherapy before surgery; surgery remains a practical fallback when anatomy prevents catheter or foam treatment.
Closing one vein does not remove the tendency to develop reflux elsewhere. Residual tributaries, reopening of the treated segment or new varicose veins can require later assessment or treatment.
Recovery, poor candidates and warning signs that change the decision
Recovery often favours catheter-based treatment: endovenous laser ablation and radiofrequency ablation usually involve tiny access wounds, walking soon afterwards and bruising rather than surgical incisions. Foam sclerotherapy and ambulatory phlebectomy also tend to allow quick return to activity, but repeated treatment can be necessary. Compression reduces aching and swelling; it does not correct refluxing veins.
| Option | Recovery and practical risk | When it changes the choice |
|---|---|---|
| Laser or radiofrequency ablation | Short recovery; risks include bruising, burns and temporary nerve symptoms | Choose only when ultrasound shows an accessible refluxing trunk |
| Foam sclerotherapy or phlebectomy | Usually little downtime; foam can cause inflammation, pigmentation or visual symptoms | Useful for selected branches, but tortuous anatomy can favour foam over a catheter |
| Ligation and stripping | More incisions, wound care and activity restriction; later veins can still develop | Consider when anatomy or access makes ablation and foam unsuitable |
Delay elective treatment during pregnancy, and discuss alternatives if you have active skin infection, poor arterial circulation, immobility or a history that raises clotting risk. A specialist should adjust the plan after examining pulses, skin and duplex findings.
Seek urgent medical help for sudden one-sided leg swelling, warmth, redness or severe calf pain; chest pain, breathlessness or coughing blood may indicate a pulmonary embolism. After treatment, report heavy bleeding, fever, rapidly increasing pain or a cold, pale or numb foot. These warning signs change the decision from cosmetic treatment to prompt medical assessment.
Frequently asked questions
How do spider veins differ from reticular and varicose veins?
Spider veins are fine red, blue or purple lines. Reticular veins are wider, bluish veins beneath the skin. Varicose veins are raised, twisted veins that can cause aching, heaviness, itching or ankle swelling.
What does a specialist check before recommending varicose vein treatment?
A specialist checks vein width, shape, depth, symptoms, skin changes and blood flow. Duplex ultrasound can show superficial venous reflux and help guide treatment selection.
Which treatments suit spider veins, surface veins and tortuous varicose veins?
Sclerotherapy is commonly considered for many spider and reticular veins. Surface laser treatment can suit selected small veins. Larger, tortuous or refluxing veins require assessment for ablation or surgery.
How do laser treatment, radiofrequency ablation and surgery differ?
Laser and radiofrequency ablation close a refluxing vein from inside a catheter, while surgery removes or ties off selected veins. The choice depends on ultrasound findings, vein anatomy, symptoms and recovery priorities.